Action Point 5 - Strategy to facilitate reliance

Last update: 05/09/2026

Background

The South-East Asia Regulatory Network (SEARN) was created in 2016 by the 11 Member States of the WHO South-East Asia Region to develop and strengthen regulatory collaboration, convergence and reliance in the South-East Asia region over shared regulatory issues and challenges.

One of the main objectives of the network is to ‘Identify and develop potential work sharing and reliance processes to help address common work areas and optimize use of existing regulatory capacities and expertise available in the region.’

To address this need, the Assembly created in 2022 a dedicated action point (AP5) in the SEARN workplan, led by Working Group 2 (WG2) Regulatory Strengthening.

Scope and definitions

In 2021, the WHO Expert Committee on Specifications for Pharmaceutical Preparations adopted as an annex to its 55th report the Good reliance practices in the regulation of medical products: high level principles and considerations.

This document defines reliance as ‘The act whereby the regulatory authority in one jurisdiction takes into account and gives significant weight to assessments performed by another regulatory authority or trusted institution, or to any other authoritative information, in reaching its own decision. The relying authority remains independent, responsible and accountable for the decisions taken, even when it relies on the decisions, assessments and information of others’.

As Figure 1 describes, reliance may take many forms and be applied to varying degrees in recognizing or taking account of the assessments, decisions or other authoritative information of other authorities and institutions. While recognition may be seen as a special and more formalized approach to reliance, whereby one regulatory authority recognizes the decisions of another regulatory authority, system or institution, obviating additional regulatory assessment to reach its own decision. Recognition usually requires formal and binding legal provisions.
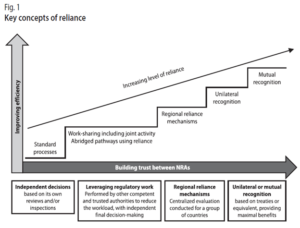
Reliance may be used in the regulation of any of the medical products in the scope of SEARN and for all regulatory functions, in the full life cycle of a medical product.

While the precise situations in which reliance may be used are to be defined at the national level, some conditions are required to enable reliance, including having access to sufficient information from the reference NRA such as full/public assessment reports in a common language documenting their regulatory decisions.

General objective

To facilitate reliance in the SEARN region.

Enabling reliance in the region

Prioritized areas for reliance

The prioritized areas were selected considering the results from a survey conducted during the 2022-2023 work plan. It was decided that this strategy would focus on:

  • medicines and vaccines,
  • For Marketing Authorizations, Vigilance, Regulatory Inspections, and Laboratory Testing.

Converging on the definition of reference regulatory authorities in SEARN

The WHO Good reliance practices in the regulation of medical products: high level principles and considerations define a reference regulatory authority as a ‘national or regional authority or a trusted institution such as WHO prequalification (WHO PQ) whose regulatory decisions and/or regulatory work products are relied upon by another regulatory authority to inform its own regulatory decisions’.

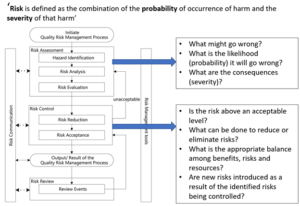
The guidelines further highlight that ‘Each NRA should define its own strategy for an appropriate risk-based approach to reliance, which includes factors such as the type and source of products evaluated, the level of resources and expertise available in the NRA, the public health needs and priorities of the country and opportunities for reliance’.

Further information on Quality Risk Management can be found in ICH Q9(R1) – 2021 and in the 2013 WHO guidelines on Quality Risk Management. The approach is summarized in the below diagram derived from ICH Q9(R1):
When identifying a reference regulatory authority, the below principles can be followed:

  • It should be based on objective criteria, including evidence that the authority can be trusted (e.g. WLA, benchmarking, audit, accreditation, other information about the actions taken by an NRA), and the possibility to access the minimum required information in a language that is understood or can be easily translated.
  • It should consider the capacity of the reference NRA to conduct the regulatory function independently (e.g. maturity level, or technical capacity to review further a dossier) and the capacity of the relying NRA compared to the reference regulatory authority to conduct the activities of a certain function (i.e. can the reference NRA do the assessment as well or better than the relying NRA? However, a minimum level of ML3/4 or WLA should be expected)
  • It should be specific to one particular type of products and regulatory function (e.g. an authority may be ML3 for vaccines but not for medicines, or ML4 for vigilance but ML1 for marketing authorizations)
  • It should be reconsidered regularly based on experience (e.g. for Marketing Authorizations, considering the frequency of substandard and falsified products).
  • As a best practice, the relying NRA when applying reliance, should at least verify sameness. A checklist and guidance to conduct verification of product sameness for NRAs to use as reference can be found in the Appendix 2 of the 53rd report of the WHO Expert Committee on Specifications for Pharmaceutical Preparations (page 259) for Marketing Authorizations and Regulatory Inspections)
  • It is recommended to publish on the NRA website a guideline on reliance, which defines the scope, criteria and principles followed to select reference authorities and how such assessment will be used, together with information which may be updated more regularly on which are the accepted reference regulatory authorities (for one particular type of product/function or type of decision). This will help stakeholders to comply with the NRA’s expectations.

Possible Criterion for selecting a Reference Regulatory Authority

In the context of the prioritized functions, the table below presents some examples of criteria which may be considered to define the relying strategy:

Regulatory functionPossible Criterion for selecting a Reference Regulatory Authority
Marketing Authorizations
  1. Evidence of the strength of the regulatory system of the reference authority:
    • (t)WLA for the type of product and MA (RI may also be considered),
    • ML3 or ML4 for the product and MA (RI may also be considered),
    • Stringent Regulatory Authority definition/ICH membership
    • PIC/S membership (providing reassurance on the compliance of local production with cGMPs)
    • WHO Prequalified products,
    • experience (e.g. an advisory committee’s recommendation, frequency of SF products identified from this country, whether another strong regulatory authority relies on this authority, evidence of the performance of the reference regulatory authority etc.)
  2. Information on the Reference authority’s decision-making system:
    • by whom,
    • is there an expert committee, etc.
  3. Relative strength: does the reference regulatory authority have similar or stronger capacity for assessing this product compared to the relying authority? (minimum Maturity level 3 against the GBT)
  4. Availability of the minimum required information from the NRA (e.g. website, MoU, CDA) or the applicant.
  5. Responsiveness of the authority when contacted and ease of communication.
Vigilance
  1. Evidence of the strength of the regulatory system of the reference authority:
    • (t)WLA for the type of product and VL,
    • ML3 or ML4 for the product and VL,
    • Stringent Regulatory Authority definition/ICH membership,
    • experience (e.g. an advisory committee’s recommendation, robustness of previous safety decisions (has it been maintained or cancelled?), whether another strong regulatory authority relies on this authority, evidence of the performance of the reference regulatory authority etc.)
  2. Information on the Reference authority’s decision-making system:
    • how the safety data is assessed,
    • by whom,
    • is there an expert committee, etc.
  3. Relative strength: does the reference regulatory authority have similar or stronger capacity for assessing this product compared to the relying authority?
  4. Availability of the minimum required information from the NRA (e.g. website, MoU, CDA) or the applicant
  5. Responsiveness of the authority when contacted and ease of communication
Regulatory Inspections
  1. Evidence of the strength of the regulatory system of the reference authority:
    • (t)WLA for the type of product and RI,
    • ML3 or ML4 for the product and RI,
    • Stringent Regulatory Authority definition/ICH membership,
    • PIC/S membership,
    • experience (e.g. an advisory committee’s recommendation, whether other strong regulatory authority rely on this authority, evidence of contradiction with the outcome of other regulatory authorities’ inspections, evidence of the performance of the reference regulatory authority etc.)
  2. Information on the Reference authority’s decision-making system:
    1. Who can inspect
    2. How are inspectors trained
    3. Categorization of the deficiencies and follow up of the regulatory actions
  3. Relative strength: does the reference regulatory authority have similar or stronger capacity for assessing this product compared to the relying authority?
  4. Availability of the minimum required information from the NRA (e.g. website, MoU, CDA) or the applicant
  5. Responsiveness of the authority when contacted and ease of communication
Laboratory Testing
  1. Evidence of the strength of the regulatory system of the reference authority:
    • (t)WLA for the type of product and LT,
    • ML3 or ML4 for the product and LT,
    • Stringent Regulatory Authority definition/ICH membership,
    • WHO prequalified laboratories
    • ISO/IEC 17025: 2017 for laboratory testing
    • ISO/IEC 17025: 2017 for laboratory instrument calibration
    • ISO 17034:2016 for Reference Standard
    • Recent satisfactory proficiency testing reports or inter-laboratory testing reports on the scope of interest experience (e.g.whether other strong regulatory authority rely on this NCL, evidence of the performance of the reference regulatory authority etc.)
    • Any other international or national accreditation
  2. Relative strength: does the reference regulatory authority have similar or stronger capacity for assessing this product compared to the relying authority?
  3. Availability of the minimum required information from the NRA (e.g. website, MoU, CDA) or the applicant (please see section 8.4)
  4. Experience (e.g. Responsiveness of the authority when contacted and ease of communication)

Useful links

Types of decisions for which reliance may be used within the prioritized functions and sources of information

For each prioritized areas, a diversity of decisions for which reliance may be used was identified. Beyond, reliance can also be used for capacity development (e.g. when developing a new guideline or a new SOP, one Member may use the document from another country as a reference or as a starting basis).

For Marketing authorizations for medicines and vaccines, reliance may be used for:

  • Initial marketing authorizations, including product information
  • Renewal of marketing authorizations
  • Variations, including e.g. new indications or changes in the posology
  • Suspension, withdrawal of a Marketing Authorization

For Vigilance for medicines and vaccines, reliance may be used for:

  • Safety signal detection and assessment
  • Safety variations, including changes in the SmPC and patient information leaflet
  • PSUR assessment
  • Risk communication (e.g. Dear doctors letters, Direct Healthcare professional communications)
  • Risk management plans
  • Benefit-Risk reviews

For Regulatory inspections for medicines and vaccines, reliance may be used for:

  • GxP compliance, including initial assessment and maintenance
  • Information for risk-based planning of inspections, e.g. history of recalls

For Laboratory testing for medicines and vaccines, reliance may be used for:

  • Quality test results (prior or after registration/marketing)

For Market control and surveillance: while information sharing is critical for market control and surveillance, no regulatory decision could be identified for which reliance would be used, as this activity is national in nature. Associated decisions for which reliance may be used, such as benefit-risk reviews or testing, have already been addressed.


Overall, initial discussions highlighted that for the above decisions, possible sources of information, could include:

  • Applicants
  • Other NRA websites and WHO website (e.g. for prequalified products or guidelines)
  • Documents directly provided by other NRAs (e.g. un-redacted assessment report)
  • The collaborative registration procedure (CRP)

Minimum information required for reliance

The below document was developed to support the implementation of this strategy. There would be 2 main usages of this information:

  • Recommendations to guide relying countries on what is required as a minimum for them to be able to rely on other organizations.
  • Recommendations to SEARN countries on what to publish/make available (in relation with AP3 information sharing and AP4 internal platform) in order to facilitate reliance from other countries on their own decisions.

Acknowledging that the implementation of these recommendations may require addressing practical and technical challenges, and in some cases further discussions and agreement of other authorities, the adoption by the Assembly of SEARN will be followed by an implementation period of two years.

The information identified in the below table intends to present the minimum information required for reliance. For reliance, the ultimate requirement is that the relying NRA should have sufficient trust in the reference authority to use the output of their work in their own regulatory decision-making system. Abridged assessment may require additional information.

Reference organisations currently used in the region

A survey was conducted to identify the reference organizations currently used in the region. The scope was medicines and vaccines only. The survey was divided between reference organizations for Marketing Authorisation/Regulatory Inspections and Laboratory testing.

Highlights:

  • Legacy remains an important driver regarding the choice of reference regulatory authorities, and the status of Stringent Regulatory Authorities (SRA) remains the main factor associated with reliance in the region
  • Some inconsistencies have been observed. For example only one Member indicated relying on Saudi Arabia while its regulatory system reached Maturity Level 4 for both medicines and vaccines. Another example was that despite its SRA status, not all relying Members identified Health Canada.
  • Some other uncertainty or inconsistencies were observed. For regulatory inspection, only some PIC/S members are relied upon, not all.
  • Overall, the intra-regional reliance is very low.
  • A lower level of reliance was reported for Laboratory testing, which could either reflect less reliance or the profile of those who responded to the survey. Similar inconsistencies and low intra-regional reliance was observed.

Reference organisations for SEARN

Based on the results from the survey and further discussion, it was agreed for the purpose of the mapping of the sources of information for reliance prioritize reference regulatory authorities as follows:

  1. EMA (pilot)
  2. TGA
  3. US FDA
  4. MHRA
  5. Japan
  6. SwissMedic

SEARN Reliance map

SEARN developped a reliance map which contains publicly available information from Reference Authorities / Organizations commonly used by SEARN Members to facilitate reliance:

WHO-Listed Authorities

WHO has developed the WHO-listed Authorities (WLA) framework to develop a transparent and evidence-based pathway for identifying regulatory authorities operating at an advanced level of performance. One of the main goal of the WLA framework is to facilitate reliance, and there is a strong expectation of transparency and information sharing for WLAs.

In this context, it was proposed to develop and implement a survey intended for WLAs in order to continue the mapping exercise and explore possibilities to access non-public information for SEARN members.

Survey to WLAs

A survey to WLAs was developped. This survey builds on good regulatory practice principles and enablers, and especially transparency and regulatory cooperation which are integral to the WLA initiative.

This survey will be shared annually to provide an opportunity to review and update information previously shared with SEARN. Future iterations will focus primarily on confirmation/incremental updates, once baseline information has been established (e.g. ensuring hyperlinks remain valid).

The survey is divided in two parts:

  • Public information which can be used for reliance
  • Non public information which may be accessed through other means on request of foreign regulatory authorities.

The survey will be piloted with SwissMedic and TGA Australia, with direct reporting to WG2.

Ensure adequate utilization of the SEARN reliance map

A module on the use of the SEARN reliance map will be developed an included in the future training programmes developed by the relevant RCOEs.

SEARN convergence mechanism

The proposed SEARN convergence mechanism was developed following consultation in SEARN and studying experience from other regions (the EU, the ACCESS consortium), and a consultation of the industry.

Preliminary informal consultation with industry

A preliminary informal consultation in WG2 was organized on 21 April 2025 with industry to hear about industry’s perspectives on the proposed SEARN convergence mechanism, especially in terms of feasibility, expectations, and interest. Representatives included innovative manufacturers, generic manufacturers, as well as importers.

In general:

  • The selected industry representatives were supportive of convergence initiatives and reliance, although on the longer terms they were calling for the development of regulatory recognition.
  • These mechanisms are seen as having the potential of creating a significant impact for the industry through facilitating commercial flows of products between countries, while maintaining quality.
  • In general, the industry called for waivers/simplifications/convergence of regulatory requirements between countries for marketing authorizations (including pharmacopeial requirements) and for regulatory inspections, as well as convergence of the accepted dossier formats.
  • The industry also highlighted the importance of transparency, through clear procedures and requirements, from SEARN but also National regulatory authorities
  • It was highlighted that to fully benefit the region’s industry, these mechanisms should consider generic products. The industry also invited to consider situation where such mechanisms could facilitate access to medical products facing shortages in one or several countries.
  • Customs were identified as further important stakeholders important to facilitate export and import.
  • To facilitate collaboration between manufacturers and importers, it was suggested to create a common platform e.g. through regular meetings, to discuss certain topics such as the issue of importers’ access to registration documents, especially in case of smaller quantities, or the need for quality agreement / technical agreement between manufacturers and importers

On the specific draft proposed SEARN convergence mechanism

  • The selected industry representatives were generally supportive of the draft proposal.
  • It was suggested that the Industry should also be able to suggest products to be considered as part of this mechanism, and to link it with the shortage policies
  • Representatives highlighted the importance of providing very clear guidelines and procedures to industry and to link it with national guidelines on reliance
  • The timelines for registrations were an important issue of concern and it was suggested to consider reasonable timelines for registration as part of this mechanism, e.g. 12-18 months, and to have clear guidelines about what happens if there is some delay at any stage of the process
  • Clarity was also requested on whether health supplement and traditional medical products can be considered as part of this mechanism
  • There was a request for participations of observers from pharmaceutical associations.


Further, NRA and partners representatives highlighted the importance of developing indicators for measuring the impact of this mechanism. Regarding vigilance, it was mentioned that there should be systematic access to RMP and that MAHs/applicants should consider regional component of RMPs also considering the diversity of healthcare systems in SEARN.

Workshop with industry to finalize the SEARN convergence mechanism

On 24 November 2025 a further consultation was organized with industry to finalize the concept:

  • The proposed SEARN convergence mechanism was generally supported by Industry representatives and there were no further immediate comments

On the request of some SEARN Members, a further written consultation was conducted during which no comment was received.

Adopted convergence mechanism on marketing authorizations

The SEARN Convergence Mechanism is SEARN’s main reliance, access and worksharing mechanism.

The final concept note is presented below:

It will be piloted during the next workplan, with direct reporting to WG2. To support the pilot, a call for expression of interest will be issued to identify one or a few proposals of priority products.

The SEARN Secretariat may also reach out directly to international industry associations, other departments in WHO and NGOs to assist in identifying priority products.

Next steps

Action point concluded during the 2025-2026 work plan.

Further issues related to reliance should be monitored and discussed directly by WG2, in coordination with the relevant drafting groups and working groups. A call for expression of interest will be issued to identify one or a few proposals of priority products during the next workplan to pilot the SEARN convergence workshops. The SEARN Secretariat may also reach out directly to international industry associations, other departments in WHO and NGOs to assist in identifying priority products.